Showing posts with label Choledocholithiasis. Show all posts

Friday, April 25, 2014

Extra large diverticulae flanking ampulla

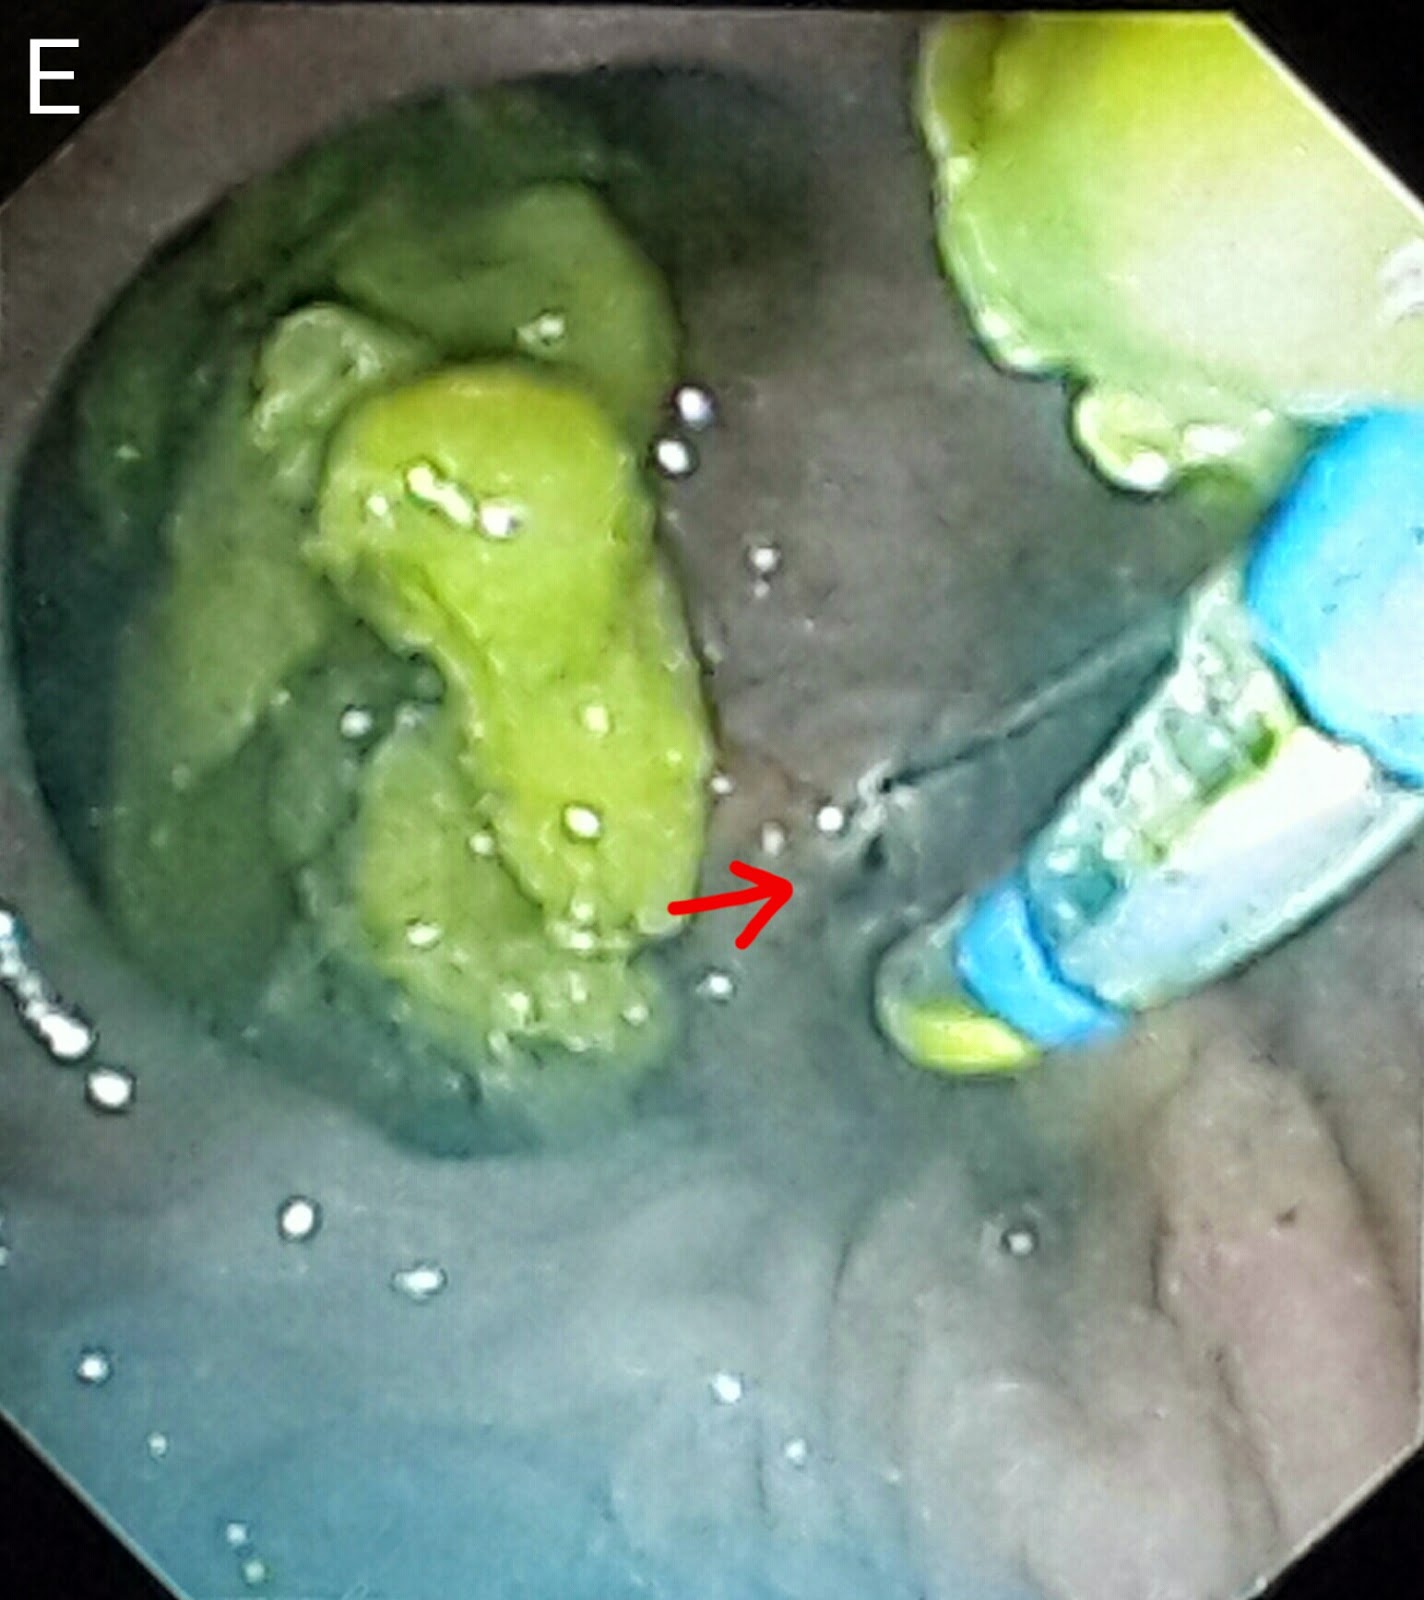
This 60 year old gentleman had been referred following the development of classical obstructive jaundice signs. His ultrasound reported an ampullary mass lesion. The CT report showed a greatly distended CBD with a large calculus at the terminal end (A: white arrow posts to the stone and black arrows delineate the CBD). There was a "whoa" moment the moment the papilla came into view as it was flanked by two huge diverticulae stuffed with food (B: red arrows. White arrow points to the papilla). The scope kept slipping and cannulating the ampulla was trickier than expected (C). Contrast injection showed a dilated CBD with a large stone near the lower end (D: black arrow). We did a small sphincterotomy (E: red arrow). A 10 French plastic stent of 10 cm length was then deployed (F1: red arrow shows the stent and blue arrow points to the stent assembly. F2: black arrows show the stent). The patient was referred to the surgeon for cholecystectomy and bile duct clearance. 

Thursday, March 6, 2014

Uncommon biliary tree anatomy

This 54 year old lady had been referred for management of choledocholithiasis prior to undergoing a cholecystectomy. The ultrasound report suggested a single stone in the mid CBD. Initial contrast injection outlined the stone (A: white arrow). Things were about to get interesting, however as further contrast made the picture clearer. We could now see the stone (B: white arrow), the cystic duct (B: blue arrow) and what appeared to be a dividing line right in the middle of the CBD (B: red arrow). And even more contrast finally showed us what we were dealing with: double common bile duct with a common opening with the stone in the left stem (C: white arrow), right and left hepatic ducts draining separately into right and left bile ducts (C: yellow arrows), the cystic duct draining into the right bile duct (C: blue arrow). The arrowheads show black areas which are actually bile ducts viewed head on (C: red arrowhead shows the entrance of the cystic duct into the right bile duct). The stone was removed with an extraction balloon after sphincterotomy (D). The last diagram (E) shows the the modified classification of extrahepatic bile duct duplication as proposed by Choi et al.. Ours seems to be a Va type. The important thing here is the clear communication of this abnormal ductal anatomy to the surgeon who will be doing her cholecystectomy so as to prevent any inadvertent ductal injury and compromised drainage of any of the hepatic lobes.
Friday, February 7, 2014

A balloon for every stone

This 50 year old lady had undergone cholecystectomy twenty years earlier. She had now been having recurrent bouts of right hypochondrial pain. An ultrasound scan showed a 12mm stone impacted in the distal CBD. We were greeted by a big fat papilla with the orifice at its lower end (A: white arrow). Multiple attempts to cannulate the CBD were unsuccessful. We decided to do a precut with a needle knife (B). It was a textbook precut and the CBD opening was nicely exposed (C: white arrow shows the CBD opening - somehow appearing suspiciously similar to the Superman insignia). Contrast injection showed two stones, one below the scope and another just above it (D: white arrows). The papillotomy was extended (E) , however the size was insufficient considering the size of the stones. Our next step was to do a sphincteroplasty using an 18mm diameter TTS balloon (F: white arrow shows the waist of the inflated balloon at the ampulla). Following this, two stones were successfully extracted (G1 & G2). A final cholangiogram with an inflated balloon just above the ampulla showed a duct clear of stones (H).

Wednesday, January 29, 2014

Retained CBD stones post cholecystectomy

This lady was referred to us from another hospital. A T tube had been placed following cholecystectomy the post operative ultrasound and T tube cholangiogram suggested that there was a retained stone in the CBD. Contrast injection identified a negative shadow in the upper CBD (A: blue arrow. White arrow marks the T tube). We removed the T tube and performed a balloon sweep which resulted in not one but two stones (B1 & B2: white arrows. The second was a perfectly cut diamond!). An occlusion cholangiogram with contrast injection over a fully inflated balloon (C: white arrow) showed a clear CBD.

Tuesday, January 28, 2014

Tackling a large stone in an old lady

his 80 year old lady had presented with a common bile duct stone (bit unusual in her age group if our past experience was anything to go by). The ampulla was quite swollen (A :white arrow). Contrast injection showed a stone in the upper CBD (B: white arrow). We did a large papillotomy (C: white arrow), keeping in mind the size of the stone. The first attempt at stone extraction was made using a balloon which was maneuvered
across the stone (D: white arrow & E: white arrow shows the balloon inflated behind the stone, marked by the red arrow). The balloon kept slipping past the stone (F: white arrow shows the balloon which has slipped below the stone, marked by the red arrow). We went for the basket next (G: white arrow points to the open basket next to the stone, indicated by red arrow). This was successful and the stone was finally extracted (H1 & H2). Quite large and almost a perfect cylinder (I). Shotgun slugs, anyone?


Thursday, January 2, 2014

Bile duct injury and calculi post cholecystectomy

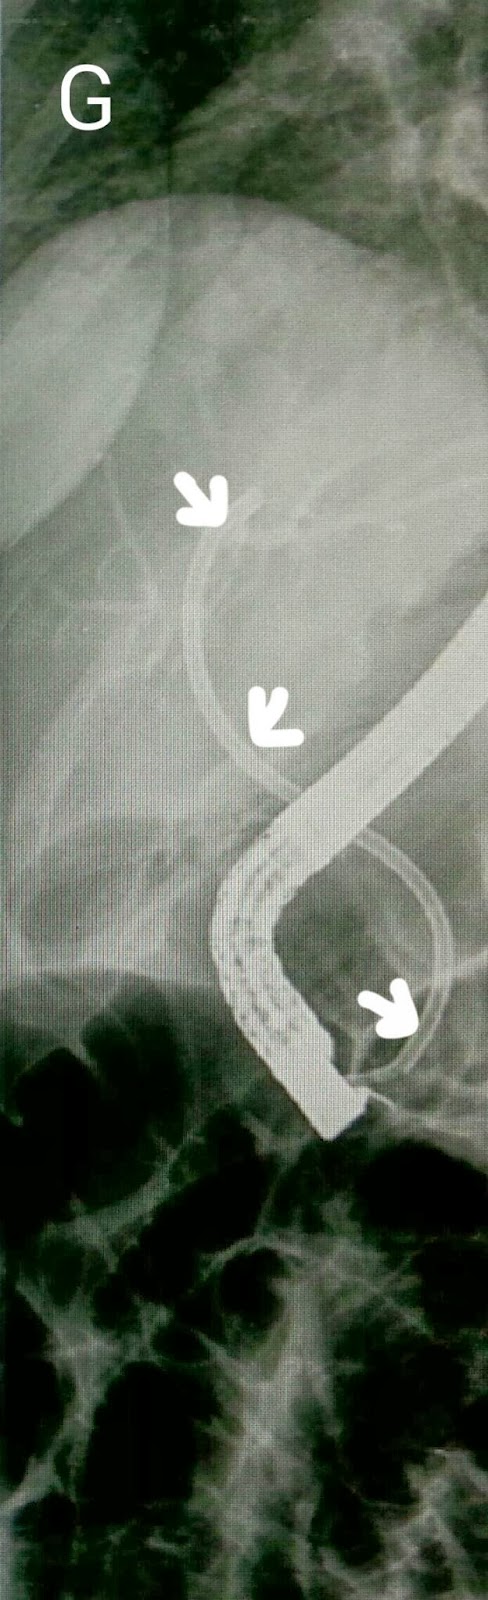
This 35 year old lady had undergone a laparosocpic cholecystectomy at another hospital three months ago. She had been re-admitted with an acute abdomen and the surgeons reported a rent in the CBD and placed a T-tube. She was then referred to us for CBD stenting. Her T-tube cholangiogram showed leakage of contrast (A: white arrow) and what appeared to be a stone (A: red arrow). Contrast injection on ERCP confirmed the cholangiogram findings and showed both the leak and the stone (B: white and red arrows respectively). Curiously, the T-tube was not outlined and we Suspected that it may have gotten dislodged. We did a wide papillotomy (C) and swept the CBD with a stone extraction balloon (D) which yielded a stone (E: white arrow). An occlusion cholangiogram an inflated balloon (F: white arrow) showed a clear CBD. We ended the procedure by placing a 12 cm long single pigtail stent of 10 French diameter (G: white arrows). Single pigtail stent being necessary to anchor the stent inside the CBD keeping in mind the wide papillotomy that had been done. 

Friday, December 27, 2013

Stone extraction impeded by infra-diverticular ampulla and narrow CBD

This 72 year old lady had been referred for a stone extraction. Our typical biliary stone patients are usually much younger females. Going in, we were greeted by an infra-diverticular ampulla (A: white arrow). The ampulla was at the edge of the diverticulum. Such ampullas are difficult to cannulate and have a tendency to keep sliding over the edge of the diverticulum. Once cannulation was achieved, contrast injection showed a large stone in a very prominent CHD (B: white arrow) and a prominent CBD (B: blue arrow) with a tapered lower end. The position of the ampulla restricted the extent of our papillotomy (C: white arrow). One can easily end with an intestinal perforation if too "courageous" with papillae that lie on the borders of diverticuli. Keeping in mind the size of the stone, the patient's age, the narrowed lower CBD and limited papillotomy, we decided to pass a plastic stent of 10 French diameter and 12 cm length (D: white arrows).

One for the Stonehenge: An unusually large CBD stone

This 35 year old lady was one of our staple cases: CBD clearance before undergoing cholecystectomy. The ultrasound report mentioned multiple CBD stones. Contrast injection on ERCP seemed to confirm the ultrasound report with a long line of negative shadows in the CBD (A: white arrow). Once we had done a papillotomy and proceeded to retrieve some of the stones with extraction balloon, we realized that we were dealing with one very large stone. It just kept coming and coming (B & C: white arrows. Blue arrow indicated the balloon). All that was left was a very wide open papilla (D: white arrow) and further balloon sweeps were clean. The calculus filled the duodenal lumen (E: white arrows). Reminds me of the menhirs from the quarry of a certain indomitable Gaul.

Sunday, October 27, 2013

The stone that wouldn't come out

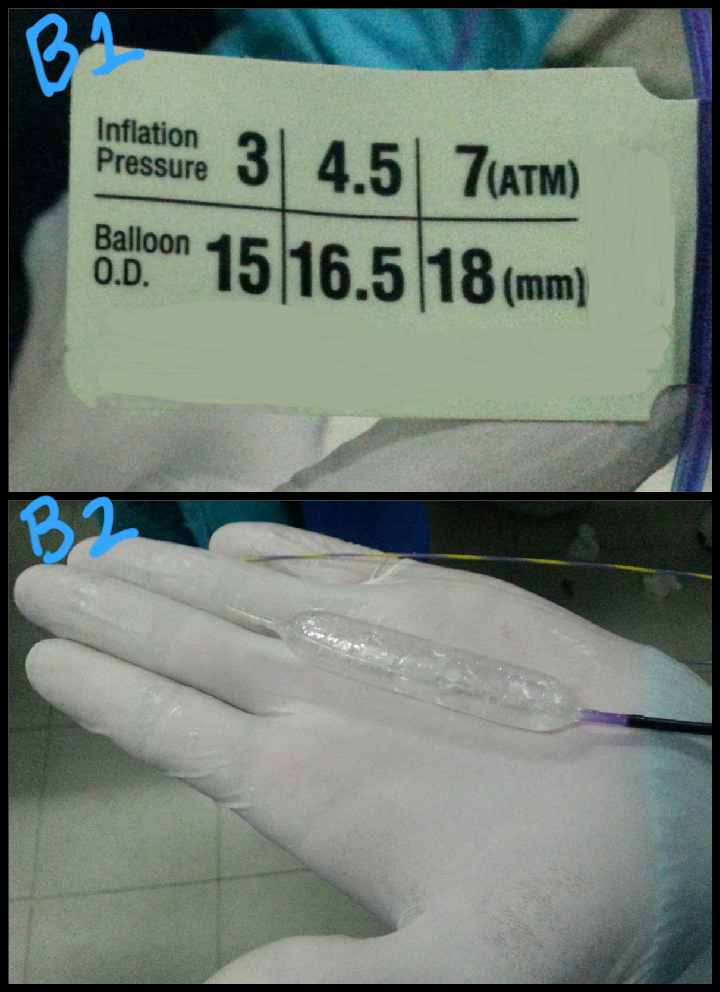
This 28 year old gentleman had what appeared to be "a soft mass with acoustic shadow" in his distal CBD. Contrast injection on ERCP showed a rounded stone in the mid CBD (A: green arrow). After a wide papillotomy, we attempted to extract the stone with an extraction balloon but were unsuccessful. We decided to do a sphincteroplasty with a wire guided balloon (B1 & B2: the balloon specifications and inflation check prior to insertion. C1 to C4: the balloon being placed into the papilla and inflated. C5: green arrows show the extent of dilated balloon on fluoroscopy). Even after sphincteroplasty, the stone could not be removed with the extraction balloon and we could clearly see it stuck in the CBD through the wide papillotomy (D: green arrow). We then decided to use the extraction basket to remove the lodged stone (E: white arrows show the open basket in the CBD). This was rewarded with success and the stone was removed (F: green arrow shows the stone, smeared with blood, lying in the duodenal lumen). 

Second (actually 3rd) ERCP for post transplant biliary leak

This 60 year old gentleman had earlier undergone ERCP and stenting for an anastomotic biliary leakage a few months earlier http://ercp365.bl...